

Be the doctor. Let Chiron run the claim.
A California workers’-comp visit asks one physician to be five people at once. ChironAI™ OM is the agentic operating system that runs the rest of the claim — causation, treatment authorisation, impairment, DWC reporting, billing and every statutory deadline — reasoned and drafted by a Round Table of Digital Employees that shows its work. You review, edit and attest.
Bring one month of EORs — you keep the findings either way.
The claim at a glance.
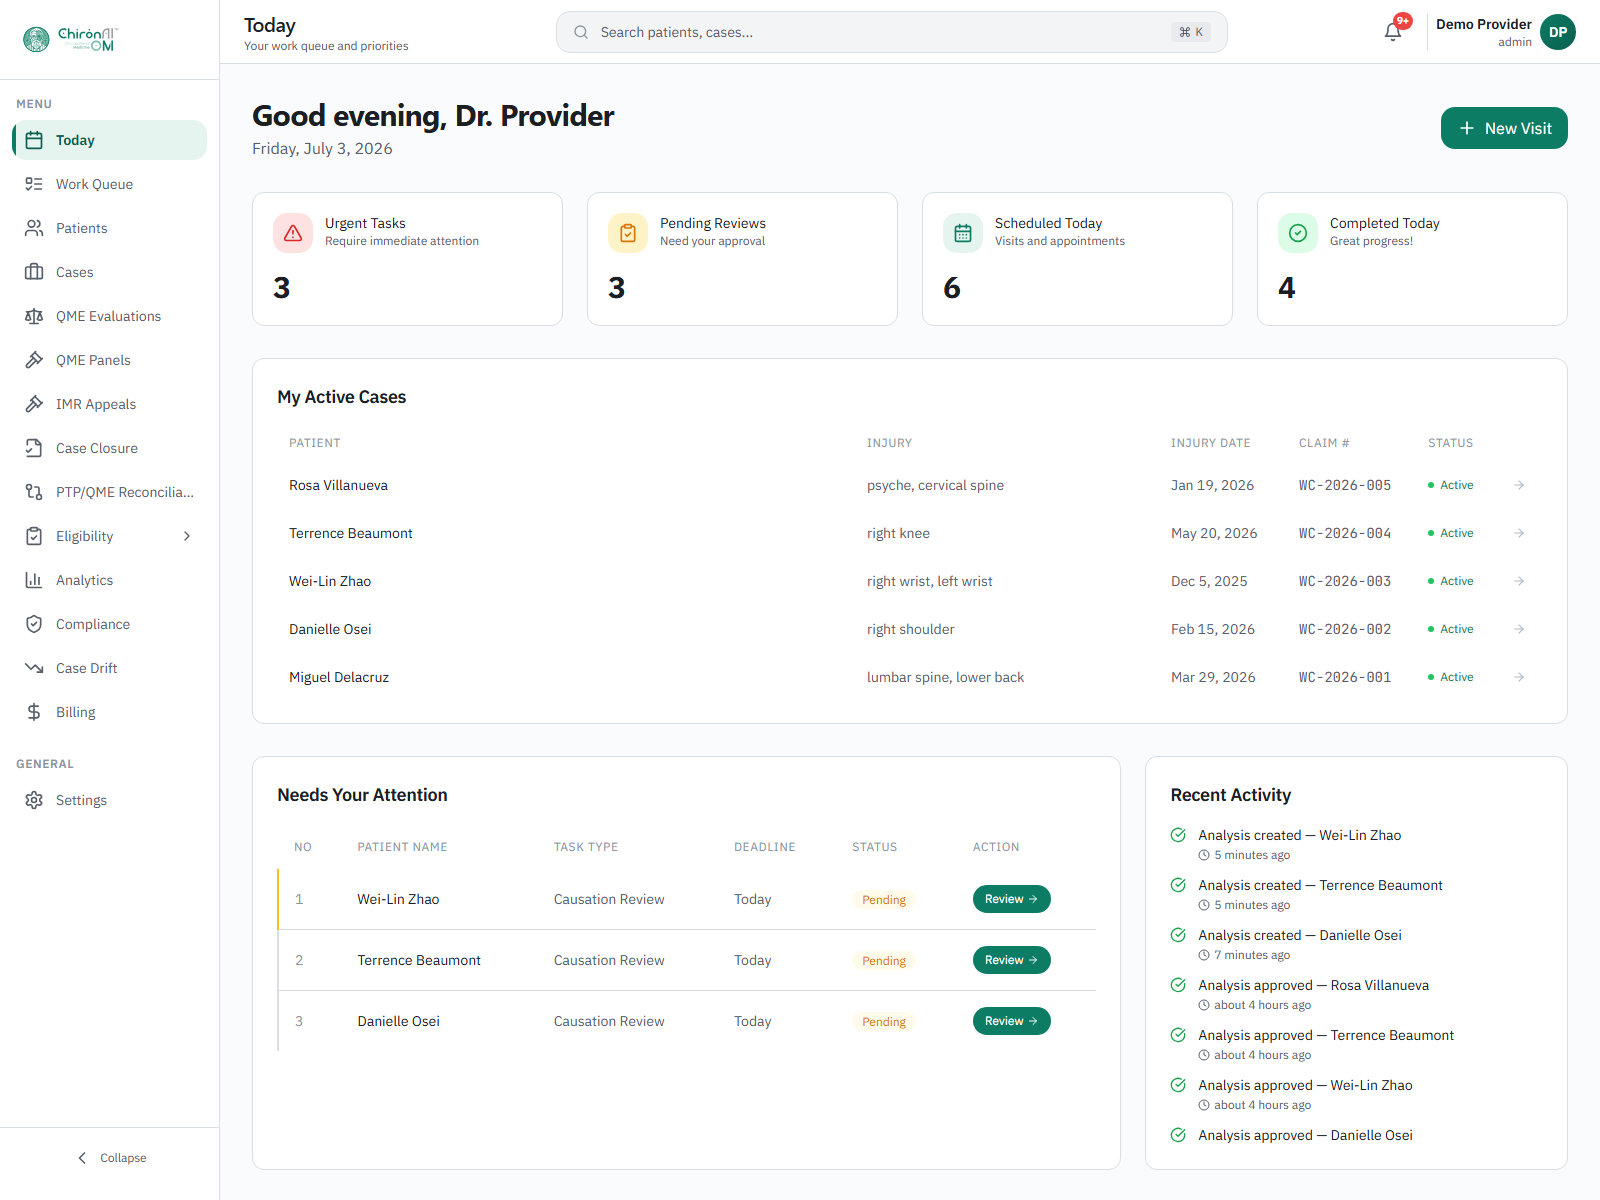
Physician-attested · Reasoning shown on every determination · Built for California WC · Generally available since August 12, 2026
ChironAI™ OM, in motion.
Four things a practice owner actually feels.
Bill for the money you are already owed
California makes late-payment penalties self-executing — 15% plus interest on a treatment bill under §4603.2, 10% plus 7% on medical-legal under §4622. Collecting it means knowing the exact receipt date on every charge and counting calendar days. The system does that; almost no practice does.
See the money path →Stop being the integration layer
One visit asks a physician to hold §4628, what is admissible under §4062.3, apportionment, MTUS and four overlapping clocks in their head at once. The reasoning layer holds them instead, and shows its working so the physician stays the one deciding.
Watch the Round Table convene →Never be the practice that missed a clock
Every statutory deadline is computed against the California holiday calendar rather than remembered — Form 5021 at five business days, PR-2 on cadence, the QME timeline, second review, IBR. A missed window is not recoverable and is entirely avoidable.
See every deadline tracked →Trust a report you did not write yourself
An entry that cannot reach a source it was given is dropped. A second pass tries to refute the first. Page citations are checked back against the page. Legal authorities come from a closed list, so an invented case citation is not a risk the system runs.
How we prevent fabrication →You trained for one of these. The claim demands all five.
The clinical work is the part you trained for, and it is the smallest part of the visit. The other four are where the hours go, where revenue leaks, and where a claim is won or lost long before anyone sees a courtroom.
Clinician
diagnose and treat the injury
Forensic investigator
establish work-relatedness and apportion cause
Regulatory clerk
author DWC reports and beat every statutory deadline
Billing manager
code to the fee schedule and chase the pay clock
Expert witness
build a record that survives deposition
Not a feature bolted onto a chart. An operating system for the claim.
Most tools in this market solve one step and hand you back the other seven. OM was built for the whole lifecycle, and the California statutory detail is implemented in the software rather than left to the physician to remember.
- 81
- capability modulesNestJS domain modules, excluding infrastructure
- 619
- API operationsHTTP route handlers across all controllers
- 137
- data domains modelledmapped tables in the schema
- 67
- statutes & regulations implementeddistinct section citations plus AB/SB statutes in shipped code
- 13
- official DWC & QME formsstate PDFs bundled with field mappers
- 5
- Digital Employees at the Round TableChiron, Justine, Eli, Issac, Theo
A specialist team, not an autocomplete.
OM runs on Eve-Healthcare f5/reasoner — a composed reasoning system rather than a single model. What matters clinically is not the engine underneath, but that the work is divided among specialists, shown as it happens, and grounded in sources you can check.
The Round Table
Five specialists. The right ones, on the right case.
Chiron leads every case. Issac assesses utilization-review and IMR exposure. Justine convenes when apportionment or mixed causation is in play, Eli when there is a billing dispute to reason through, and Theo on questions of ethics and fairness. Specialists convene on the cases that need them and stay out of the ones that do not.
Glass-box reasoning
It shows the work while it works.
A live, step-by-step trace of what is actually happening — which specialist is running, which guideline was retrieved, which source was found, and honestly when a step returns nothing. Reasoning visibility is on by default. It is the difference between a clinical instrument and a black box.
Work that outlives the tab
Start it, walk away, come back to it finished.
Long-running work runs on the server, not in your browser. Drop a stack of records, move to another patient, sign out and come back — it keeps going, and the reasoning trace is waiting where you left it rather than lost with the connection.
Grounded, never invented
Cited, or it does not say it.
Determinations are drafted against retrieved sources and the citations are validated. Where the system is not confident enough to route a document or support a finding, it abstains and says so — a confident wrong answer in a medical-legal record costs far more than a question.
Eight phases. One system. No handoff to a spreadsheet.
01
Front door
Eligibility, MPN network rules under §4616, §4600 predesignation routing, claim-type determination, and intake that reads the documents you were sent instead of asking you to retype them.
02
Exam room
Encounters, work status and restrictions, a plan of care grounded in MTUS, dictation, and a treatment plan drafted from the record for the physician to edit and sign.
03
Causation & apportionment
AOE/COE reasoning with the evidence cited, and statutory apportionment under §§4663 and 4664 — with the citations validated rather than asserted.
04
Treatment authorisation
DWC Form RFA end to end, utilization review tracked on the §4610 clock, denial exposure assessed before you file, and IMR appeal packets when a denial has to be fought.
05
Impairment rating
AMA Guides Fifth Edition — range-of-motion tables, hearing loss, pain add-on, combined values — plus PDRS rating and Almaraz/Guzman analysis where a strict rating does not fit the patient.
06
Reporting & med-legal
Doctor’s First Report, PR-2 on cadence or material change, P&S/MMI, QME panels and evaluations, information exchange under §4062.3, and per-recipient proof of service.
07
Billing & revenue
OMFS coding, the §4603.2 45-working-day pay clock with its penalty and interest engine, explanation-of-review handling, bill review and appeals.
08
Closure & defensibility
Case closure with an attested packet, a sourced chronology that preserves contradictions rather than averaging them away, and defensibility analysis before a deposition rather than after.
Every determination has your name on it. That is the design, not a limitation.
The physician decides. Always.
Chiron reads, reasons and drafts. It does not diagnose, determine or treat. Every substantive output is reviewed, edited and attested by the treating physician before it becomes part of the record — enforced in the software, not promised in a policy.
Built for the disclosure rules, not retrofitted
AI authorship is disclosed where it is material, decision authority stays with the clinician, and the persona never implies licensure. These are architectural properties of the system rather than copy on a page.
Tenant-isolated by construction
Row-level isolation in the database, role-based authorisation on clinical and financial operations, per-case access control, and an immutable audit trail on every mutation.
Your data is not training data
Customer clinical data does not enter a training pipeline. There is no path by which it could — the property is enforced at the dataset layer rather than asserted as a policy that could later be revised.
The full posture, including what we do not claim, is in the Trust Center.
Bought by one person. Used by another.
Each row says which reader it is written for, so you can skip the ones that are not you.
For the people who sign
The practice owner
Late-payment penalties in California are self-executing, and collecting them means knowing the exact receipt date on every charge. The system counts; almost no practice does. A missed statutory window is not recoverable.
See the money path →For the people who sign
The defence-side reviewer or counsel
An entry that cannot reach a source it was given is dropped. A second pass tries to refute the first. Page citations are checked back against the page, and legal authorities come from a closed list.
How fabrication is prevented →For the people who use it
The treating physician
One visit asks you to hold §4628, what is admissible under §4062.3, apportionment, MTUS and four overlapping clocks at once. The reasoning layer holds them instead, and shows its working so you stay the one deciding.
See your week with OM →For the people who use it
The QME or med-legal evaluator
AOE/COE reasoning with the evidence cited, statutory apportionment under §§4663 and 4664, and a sourced chronology that preserves contradictions rather than averaging them away.
See the causation route →It does not submit your bills. It makes them collectible.
ChironAI OM has no electronic-billing connection and does not replace whoever files your claims today. What it does is everything that decides whether the bill survives once it arrives.
Still your biller’s job
Transmitting the bill to the claims administrator, the e-billing connection itself, and the clearing-house relationship. If that already works, nothing here asks you to change it.
What decides whether it gets paid
The documentation behind the charge, the treatment checked against MTUS before it is requested, the report that survives review, and the statutory clock on what you are owed when a carrier pays late. A bill is denied for what the record does or does not say — which is upstream of anyone’s billing software.
Priced per clinician, scoped to the practice.
There is no list price to publish and we will not invent one. What is published is what the charge is based on, what every deployment includes whatever its size, and exactly how to get a number.